What does sebaceous hyperplasia look like?
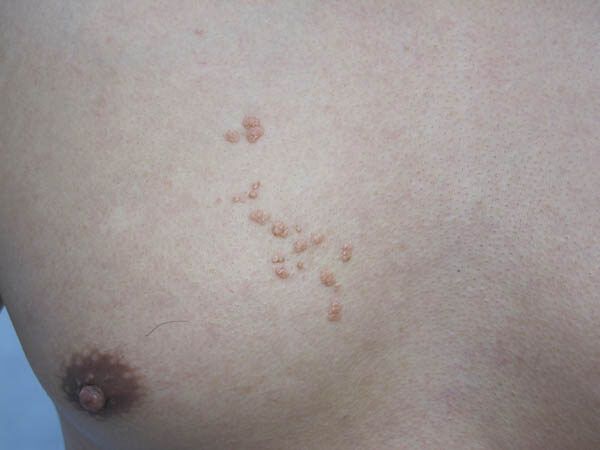


What are these yellowish bumps, actually?
Each papule is a cluster of enlarged sebaceous lobules crowded around a central follicular opening — which produces the characteristic yellowish dome with a dimpled centre. With age, the hormonal signalling that regulates gland turnover shifts, and in predisposed skin some glands respond by hypertrophying [1]. They grow slowly, multiply gradually over years, and sit precisely where makeup is hardest to smooth — the forehead and mid-cheeks — which is usually why patients finally ask about them.
Pimple, milium, or something to biopsy?
Sebaceous hyperplasia never comes to a head, never resolves, and never yields anything to pressure — three ways it declares it is not acne. A milium is firm, white and keratin-filled rather than soft and yellowish. The distinction that matters medically: an early basal cell carcinoma can mimic a sebaceous hyperplasia papule, and the pearly look-alike is the reason a physician should lay eyes (and where needed a dermatoscope) on any new or changing bump before anyone burns it off [1]. Diagnosis is quick; skipping it is how the wrong lesion gets treated cosmetically.
What actually works for sebaceous hyperplasia?
Physical removal of the overgrown gland tissue. The literature supports several in-clinic modalities — electrocautery, laser ablation and other energy-based approaches — with recent work exploring focused ultrasound specifically for sebaceous hyperplasia [1]. Removal is precise, quick and done under magnification; the practical points are lesion-by-lesion treatment, the possibility of new papules forming elsewhere over the years (the tendency is yours for life), and technique that respects the surrounding skin — this sits within Dr Sin Yong's lesion-removal work alongside platforms described on the DEKA Centre of Excellence page. Oily-skin maintenance via the SkinRev programme manages the terrain, not the lesions.
What doesn't work for sebaceous hyperplasia?
Extraction — there is nothing to extract. Retinoid creams may slightly flatten early papules but do not remove established ones. Pore strips, scrubs and “deep-cleansing” facials address blockages; this is not a blockage. And home cautery pens or acid spot treatments on the face trade a benign 3 mm bump for a permanent scar — the one outcome worse than the bump.
“Sebaceous hyperplasia is not a blocked pore — it is the gland itself, enlarged. You cannot squeeze out something that is made of you.”
— Dr Sin Yong
Dr Sin Yong’s Viewpoint
These little yellow doughnuts are harmless, but I examine every one before removing any — because an early basal cell carcinoma can wear the same disguise, and burning off an undiagnosed lesion destroys the evidence. Diagnosis takes two minutes. There is no version of this where skipping it is smart.
Prefer Not to Use WhatsApp?
Use the short enquiry form instead →
Leave your name, mobile number and email and the clinic will contact you directly. No obligation.
Prefer a preliminary view first? You can also WhatsApp a photo of the area for Dr Sin Yong to review before you decide on a visit.