What do varicose and spider veins look like?
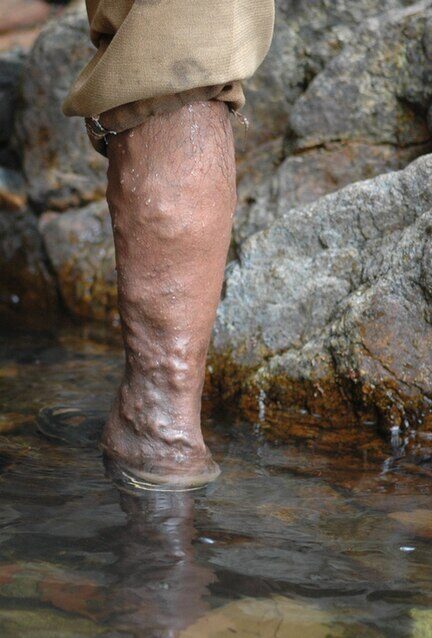

Are spider veins and varicose veins the same condition?
The internationally standard CEAP classification grades chronic venous disease from visible telangiectasias (C1) through varicose veins (C2) to swelling and skin changes at the advanced end [1,2]. The engine is valvular reflux: leg veins return blood uphill through one-way valves, and when valves fail, blood pools and pressure dilates everything downstream. Spider veins are often the visible smoke of that deeper story — which is why an assessment asks about heaviness, aching and swelling, and why bulging veins earn a duplex ultrasound before any cosmetic conversation.
When the right door is a vascular specialist
This page is deliberately honest about scope. Rope-like bulging varicosities, symptomatic legs, swelling, skin darkening at the ankles or a history of clots point to truncal reflux — the territory of a vascular specialist, where duplex-guided interventions treat the failing vein itself [1]. Dr Sin Yong will say so at assessment and refer accordingly rather than sell surface treatment over a refluxing system. Treating the visible vessels while the pressure source runs untreated delivers the classic disappointment: cleared vessels that refill within months.
Where aesthetic treatment fits
Isolated spider and small reticular veins on legs without significant reflux are the legitimate cosmetic tier — addressed with sclerotherapy (the long-standing standard for leg telangiectasias) and vascular laser in selected fine vessels [2]. Expectations are part of the treatment: leg vessels respond more slowly than facial ones, sessions are staged, and new vessels can appear over the years in predisposed legs — maintenance honesty applies. Compression, movement breaks on standing days and weight management support every tier of the spectrum, treated or not.
What doesn't work for leg veins?
Creams for varicose veins — no topical rebuilds a failed valve. Essential-oil massage — pressure on a refluxing vein changes nothing structural. Supplements marketed at 'vein health' — evidence stops well short of the claims. Crossing-your-legs folklore — posture does not cause valve failure; genetics loads that gun. And ignoring a symptomatic leg because the veins are 'just cosmetic' — aching, swelling and skin changes are the disease announcing progression, and that announcement deserves an ultrasound.
“Spider veins are often the smoke, not the fire — treat the surface while the valve below refluxes and the vessels simply refill.”
— Dr Sin Yong
Dr Sin Yong’s Viewpoint
Not every vein on this page belongs in my clinic, and I say that early. Bulging, aching, symptomatic legs need a vascular specialist and an ultrasound — treating the surface over untreated reflux just refills. The cosmetic tier is real and satisfying; my job is sorting which tier your legs are on and routing you honestly.
Prefer Not to Use WhatsApp?
Use the short enquiry form instead →
Leave your name, mobile number and email and the clinic will contact you directly. No obligation.
Prefer a preliminary view first? You can also WhatsApp a photo of the area for Dr Sin Yong to review before you decide on a visit.