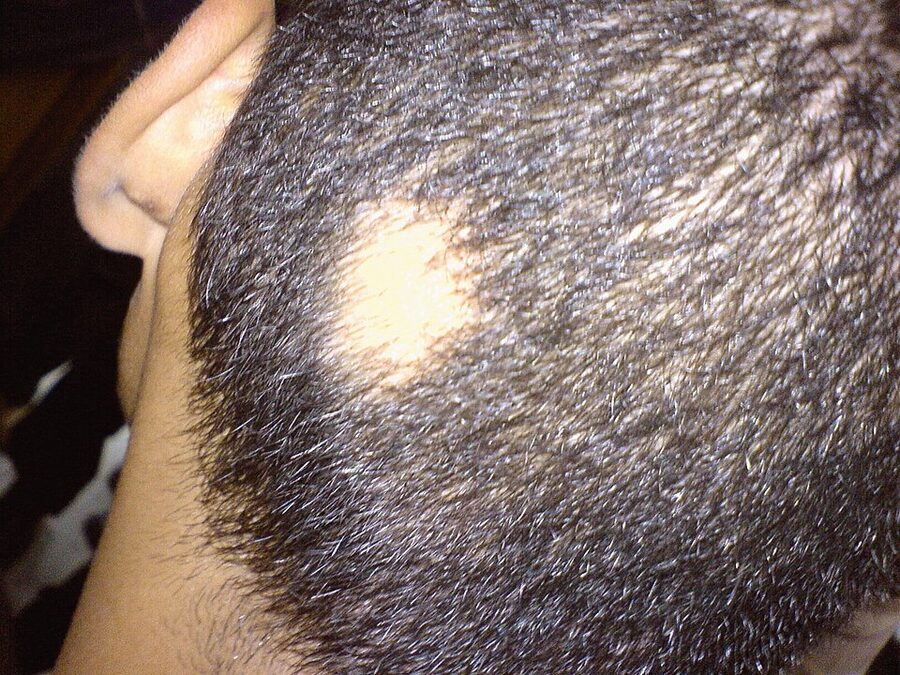
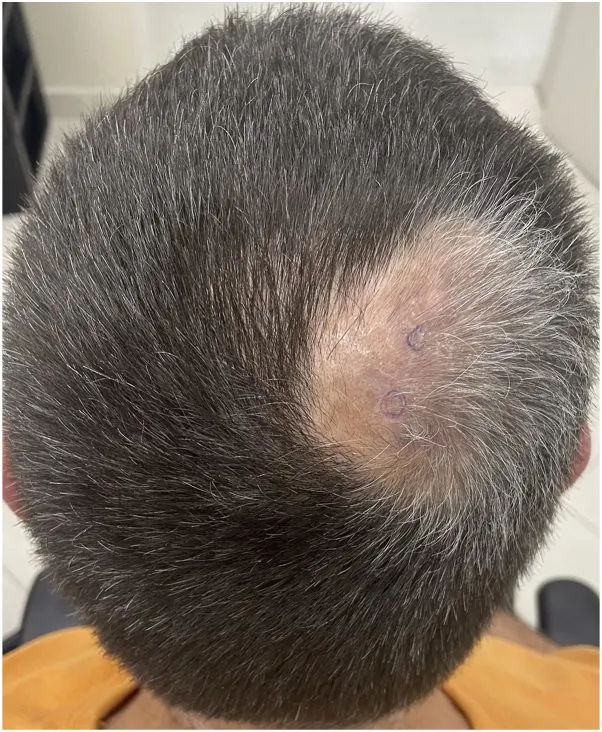
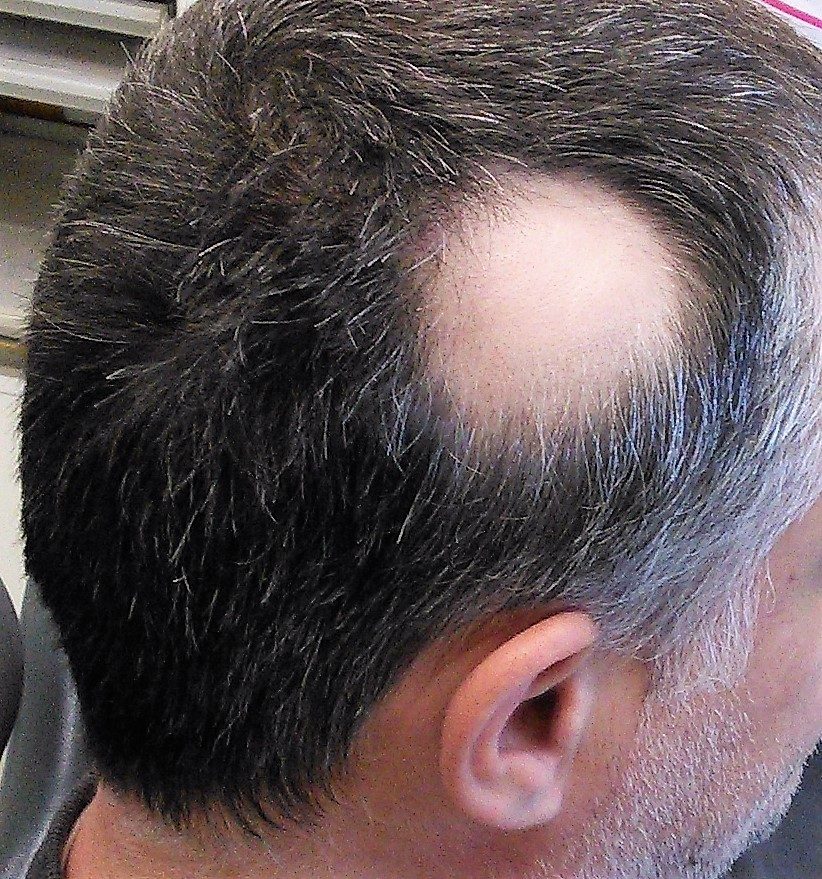
What does alopecia areata look like?
What happens inside an alopecia areata patch?
Hair follicles normally enjoy immune privilege — the immune system agrees not to inspect them. In alopecia areata that privilege collapses: T-cells swarm the growing follicle bulb and force it out of production, shedding the hair and holding the follicle in suspension [1,2]. Critically, the follicle is besieged, not demolished — no scarring, pores intact — which is why patches can regrow completely once the attack subsides, sometimes with temporarily white hair as pigment cells restart last. Triggers are debated; genetics loads susceptibility, and the condition keeps company with other autoimmune tendencies such as thyroid disease.
Reading the patterns — and knowing the neighbours
A single smooth round patch is the classic presentation; the margin sometimes shows tapered 'exclamation-mark' hairs, a diagnostic clue. Multiple or enlarging patches, loss along the whole lower hairline (ophiasis), nail pitting, or rapid diffuse loss mark more active disease and shift the management conversation. The neighbours matter: patchy loss with scaling and inflammation suggests fungal or scarring processes; diffuse shedding without patches is telogen effluvium; gradual zonal thinning is pattern loss. A patch that is red, scaly, or scarred is not areata and needs its own diagnosis promptly.
What actually works — and where this clinic stands
The evidence landscape is honest about spontaneous regrowth: limited single patches often refill within a year untreated, and first-line care — intralesional corticosteroid injections into patches, with topical agents in support — accelerates that in the literature [1,2]. Severe, extensive or rapidly progressive disease has entered a new era: JAK-inhibitor therapy, with regulatory approvals in recent years, has transformed outcomes for disease that previously had none — and belongs with specialist dermatology, to which Dr Sin Yong refers openly when the presentation warrants it [2]. This clinic's role: diagnosis (separating areata from its mimics), intralesional treatment of limited patches, thyroid and autoimmune screening conversations, and honest routing. General scalp-health support — including the approaches under hair restoration — is adjunct, never substitute.
What doesn't work for alopecia areata?
Rubbing remedies into a patch — garlic, onion juice and essential oils have folklore, not evidence, and irritating an immune-active scalp is counterproductive. Blaming stress alone — stress may time an episode; it does not explain the immunology, and stress-management is not a treatment plan. Hair fibres and concealers as a strategy without diagnosis — reasonable cosmetics, dangerous as a substitute for assessment. And panic — the single most useful sentence in areata care is that most limited patches regrow; the second most useful is that proper diagnosis rules out the conditions that don't.
“An areata follicle is besieged, not demolished — the machinery survives the attack, which is why a patch that regrows can regrow completely.”
— Dr Sin Yong
Dr Sin Yong’s Viewpoint
The most useful sentence in an areata consult is that most limited patches regrow — the follicle is besieged, not demolished. The second most useful is knowing when to refer: extensive or rapidly progressive disease belongs with specialist dermatology, where the treatment landscape has transformed in five years. My clinic's value is fast diagnosis, honest routing, and treating what is mine to treat.
Prefer Not to Use WhatsApp?
Use the short enquiry form instead →
Leave your name, mobile number and email and the clinic will contact you directly. No obligation.
Prefer a preliminary view first? You can also WhatsApp a photo of the area for Dr Sin Yong to review before you decide on a visit.